
 E-submission
 KOTA
 TOTA
 TOTS

Search
- Page Path
- HOME > Search
Systematic Review
- Definitions and assessment of residual distal radioulnar joint instability after operative fixation of distal radius fractures: a methodological systematic review
- Jae Ho Cho, Seungyeob Sakong, Sumin Lim
- J Musculoskelet Trauma 2026;39(4):323-340. Published online October 19, 2026
- DOI: https://doi.org/10.12671/jmt.2026.00290
-
 Abstract
 PDF
 Supplementary Material
- Background
Residual distal radioulnar joint (DRUJ) instability after operative fixation of distal radius fractures serves as an eligibility criterion, treatment indication, and outcome, but previous syntheses report inconsistent definitions. This methodological systematic review examined how clinical reports define, assess, and report it, and whether they distinguish it from structural triangular fibrocartilage complex (TFCC) lesions.
Methods
MEDLINE (PubMed) and Embase were searched from 2015 to 3 August 2026 for adult clinical reports in which residual DRUJ instability was assessed after fixation, or inferred from TFCC lesion characteristics, and used for a treatment decision or as an outcome. Every report entering full-text eligibility was assessed independently in duplicate; data were locked before agreement was calculated and disagreements disclosed. No riskof- bias tool was applied: neither treatment effects nor diagnostic accuracy were estimated. Findings are counts and proportions; no meta-analysis was performed.
Results
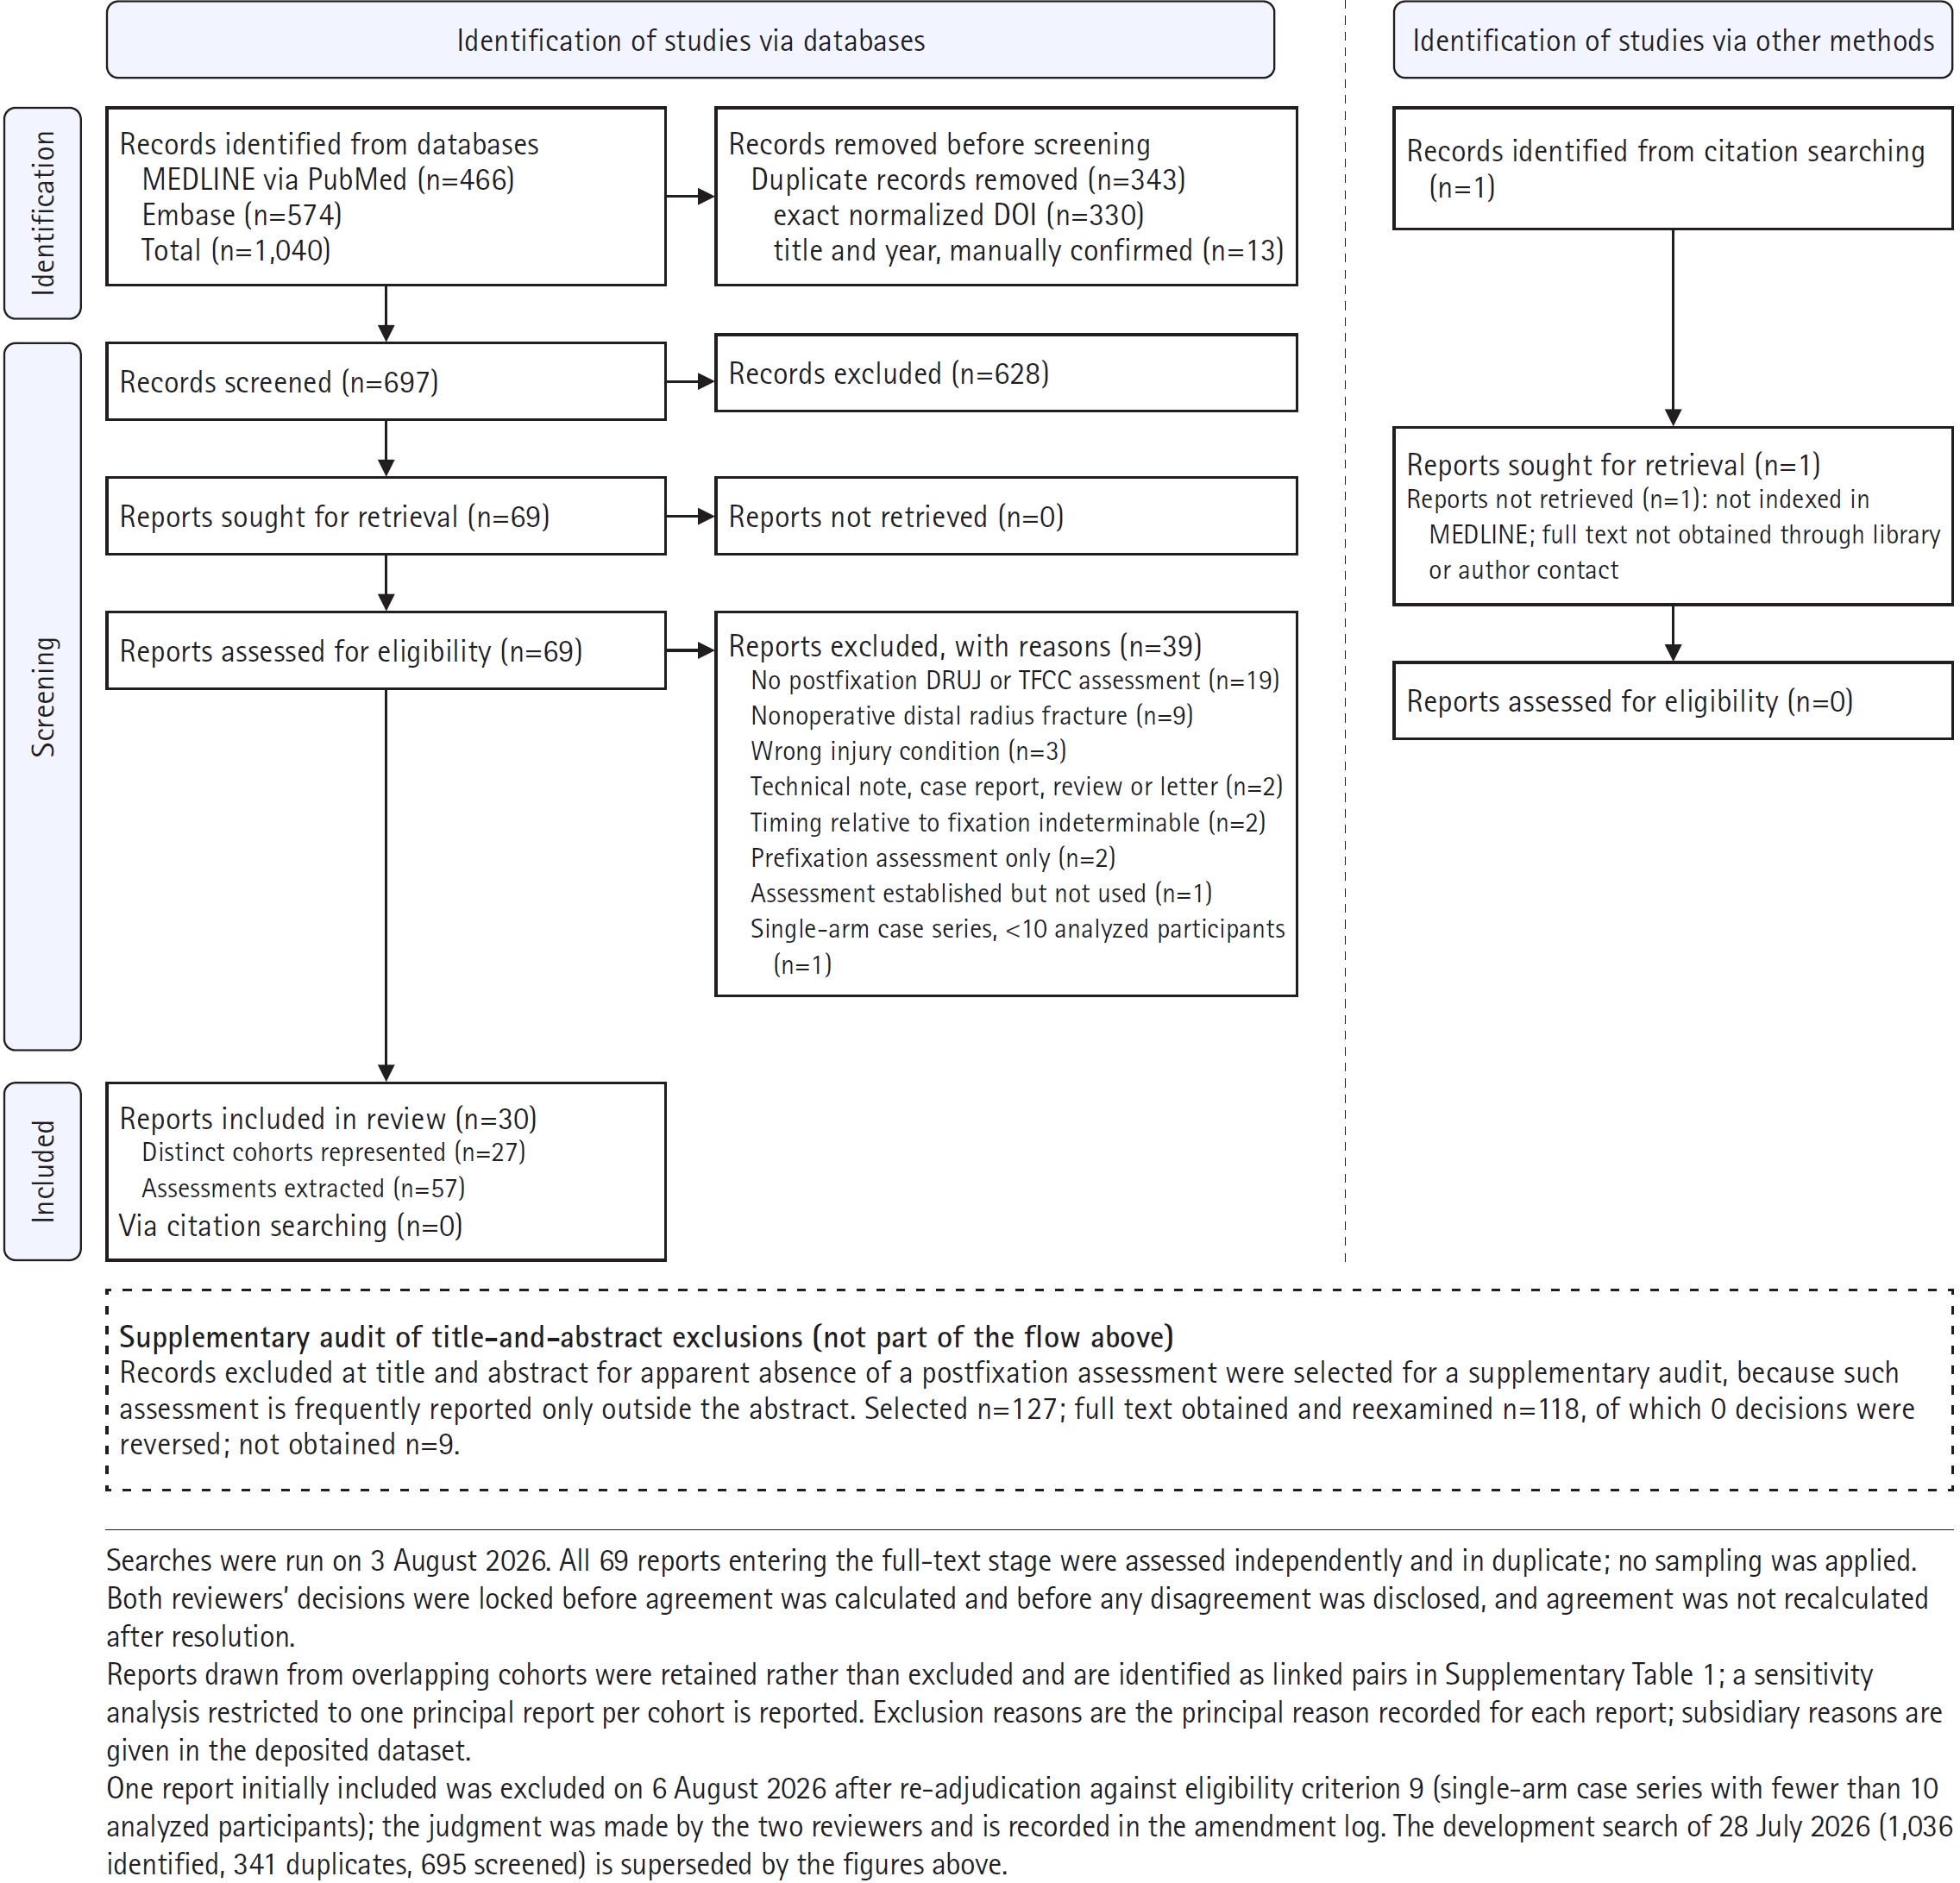
Of 1,040 records, 697 were screened and 69 assessed as full texts; 30 reports of 27 cohorts were included, contributing 57 assessments. In the treatment-decision context, 12 reports stated an operational definition (40.0% of all 30; 50.0% of the 24 containing such an assessment), four stated neither required element (16.7% of 24), and six contained no such assessment and were classified as not applicable. At the assessment level, the positive criterion was vague in 43.9% and absent in 17.5%, and explicit for 48.0% of intraoperative but 25.9% of final follow-up assessments. No report inferred instability from a TFCC lesion instead of testing the joint; one used the two constructs interchangeably, 14 (46.7%) distinguished them, and 15 (50.0%) addressed instability without structural verification. A comparable prevalence estimate was extractable from only 9 of 57 assessments (15.8%).
Conclusions
Residual DRUJ instability is therefore assessed frequently but is often incompletely defined, and until these elements are stated consistently, frequency estimates cannot be compared across studies. Level of evidence: Not applicable.
- 236 View
- 6 Download

Review Article
- Current Concepts in the Articular Cartilage Repair
- Eui Dong Yeo, Whi Je Cho, Young Koo Lee
- J Korean Fract Soc 2020;33(3):164-170. Published online July 31, 2020
- DOI: https://doi.org/10.12671/jkfs.2020.33.3.164
-
Abstract
PDF
- Articular cartilage defects are common in orthopedic practice. Most clinical and research efforts focus on restoring the damaged cartilage in connection with osteoarthritis or trauma. This article explains the current clinical approaches for repairing cartilage, as well as the research approaches and those under translation into clinical practice. Tissue engineering techniques are being employed with aims of repopulating a cartilage defect with hyaline cartilage containing living chondrocytes with hopes of improving the clinical outcomes. Cartilage tissue engineering involves the cell source, biomaterial and membranes, and growth stimulators. Tissue engineering is being applied to clinical medicine by autologous chondrocyte implantation or similar techniques. While basic science has refined orthopedic treatment of chondral lesions, available evidence does not conclude the superiority of tissue engineering methods over other techniques in improving the clinical symptoms or restoring the native joint mechanics.
- 1,350 View
- 4 Download
Case Report
- Arthroscopic Assisted Bioabsorbable Screw Fixation for Radial Head Fractures: A Report of Two Cases
- Bong Ju Park, Ki Yong An, Yong Suk Choi
- J Korean Fract Soc 2017;30(1):35-39. Published online January 31, 2017
- DOI: https://doi.org/10.12671/jkfs.2017.30.1.35
-
Abstract
PDF
- Most radial head fractures occur as the result of low-energy mechanisms, such as a trip or fall on the outstretched hand. These fractures typically occur when an axial load is applied to the forearm, causing the radial head to hit the capitellum of the humerus. Good results are shown with nonsurgical treatments for Mason type 2 fractures. However, if there is a limitation of elbow joint exercise or displacement of more than 2 mm, an operative treatment should be considered. We treated two patients with arthroscopic assisted bioabsorbable screw (K-METâ„¢; U&I Corporation, Uijeongbu, Korea) fixation for radial head fractures to prevent complications of open reduction and minimize radiation exposure.
-
Citations
Citations to this article as recorded by
- Bioabsorbable Screws Used in Hallux Valgus Treatment Using Proximal Chevron Osteotomy
Woo-Jin Shin, Young-Woo Chung, Ki-Yong An, Jae-Woong Seo
Journal of Korean Foot and Ankle Society.2018; 22(4): 181. CrossRef
- Bioabsorbable Screws Used in Hallux Valgus Treatment Using Proximal Chevron Osteotomy
- 1,453 View
- 3 Download
- 1 Crossref
Review Article
- Diagnosis and Management of Ligament Injuries of the Wrist
- Ki Tae Na, Joo Yup Lee
- J Korean Fract Soc 2016;29(2):160-170. Published online April 30, 2016
- DOI: https://doi.org/10.12671/jkfs.2016.29.2.160
-
Abstract
PDF
- The wrist joint is formed by the distal end of the radius and ulna proximally, and eight carpal bones distally. It has many ligaments to maintain stability of the complex bony structures. The incidence of ligament injuries of the wrist has increased due to sports activities. However, diagnosis and management of these injuries are sometimes difficult because of the anatomic complexity and variable injury patterns. Among them, scapholunate ligament injury and triangular fibrocartilage tears are the two most common injuries resulting in chronic disabling wrist pain. Thorough understanding of the wrist anatomy and physical and radiologic examination is mandatory for proper diagnosis and management of these conditions. This article will briefly discuss the wrist joint anatomy and biomechanics, and review the diagnosis and management of the scapholunate ligament injury and triangular fibrocartilage injury.
- 3,889 View
- 24 Download
Original Articles
- Arthroscopic Repair for Traumatic Peripheral Tear of Triangular Fibrocartilage Complex
- Seung Ju Jeon, Chan Sam Moon, Ho Seung Jeon, Haeng Kee Noh, Sung Hwan Kim
- J Korean Fract Soc 2007;20(4):330-334. Published online October 31, 2007
- DOI: https://doi.org/10.12671/jkfs.2007.20.4.330
-
Abstract
PDF
- PURPOSE
To assess the results of an arthroscopic repair for traumatic peripheral tears of triangular fibrocartilage complex (TFCC, Palmer type Ib).
MATERIALS AND METHODS
10 patients with traumatic peripheral TFCC tear were treated with outside-in technique with arthroscope and evaluated with an average follow-up of 19 months (range, 15 to 28 months). The clinical outcomes were assessed with investigation of pain, range of motion, grip strength, return to job and patient's satisfaction.
RESULTS
The arthroscopic repair of traumatic peripheral TFCC tear resulted in significant pain relief and increase in functional ability of wrist, that is, 8 excellent, 1 good and 1 fair results. At last follow-up, the average of flexion was 79° (range 76~86°), average of extension was 78° (range 70~84°), average pronation was 85° (range 75~91°) and average supination was 87° (range 79~92°). Nine patients except one were back to their original job.
CONCLUSION
Arthroscopic repair of traumatic peripheral TFCC tear could be used for pain relief and increase in functional ability of wrist.
- 988 View
- 2 Download
- Intraarticular Soft Tissue Injuries in Fractures of the Distal Radius: A Descriptive Arthroscopic Study
- Seok Beom Lee, Chang Beom Lee
- J Korean Soc Fract 2001;14(4):726-732. Published online October 31, 2001
- DOI: https://doi.org/10.12671/jksf.2001.14.4.726
-
Abstract
PDF
- PURPOSE
The aim of this study was to determine prevalence of the associated intraarticular soft tissue lesions with fractures of the distal radius by arthroscopic evaluation of the wrist joint and thus to avoid poor outcome after the conventional treatment. MATERIAL AND METHOD: Medical records, radiographs and arthroscopic findings of 27 patients with fractures of the distal radius that underwent arthroscopic procedures were reviewed . Relationships between fracture pattern and associated lesions of the triangular fibrocartilage complex (TFCC), scapholunate and lunotriquetral ligaments were investigated.
RESULTS
71% of fractures of the distal radius were associated with soft tissue lesions. Among those, tear of the triangular fibrocartilage complex was the most prevalent (47%). Associated lesions such as TFCC, scapholaunate and lunotriquetral lesion were more common with inraarticular fracture, while severe nature of the lesion that neccessiated pinning and/or arthroscopic repair was more common with extraarticular fractures of the distal radius.
CONCLUSION
Incidence of the associated soft tissue lesions in this study were comparably high with the latest publications. The authors suggest strongly that wrist arthroscopy should accompay any procedure for fractures of the distal radius, if it is to be done under anesthetic control, to get more favorable outcome. -
Citations
Citations to this article as recorded by- Arthroscopic Repair for Traumatic Peripheral Tear of Triangular Fibrocartilage Complex
Seung-Ju Jeon, Chan-Sam Moon, Ho-Seung Jeon, Haeng-Kee Noh, Sung-Hwan Kim
Journal of the Korean Fracture Society.2007; 20(4): 330. CrossRef
- Arthroscopic Repair for Traumatic Peripheral Tear of Triangular Fibrocartilage Complex
- 1,273 View
- 0 Download
- 1 Crossref
 First
 Prev



