
 E-submission
 KOTA
 TOTA
 TOTS

Search
- Page Path
- HOME > Search
Original Article
- Percutaneous Kirschner-wire fixation followed by an opencast to permit protected daily and sports activities in patients with tendinous mallet finger: a case series at a tertiary hospital in Korea
- Hyeon Jun Kim, Ji Woong Kim, Min Kyun Cho, Sung Yoon Jung
- J Musculoskelet Trauma 2026;39(4):354-364. Published online October 20, 2026
- DOI: https://doi.org/10.12671/jmt.2026.00269

-
 Abstract
 PDF
- Background
Dong-A University Hospital’s protocol for tendinous mallet finger requires 12 weeks of continuous full-time distal interphalangeal (DIP) joint splinting, which may restrict activities and complicate hygiene. This study evaluated the feasibility, short-term safety, and 6-month clinical outcomes of buried Kirschner-wire fixation followed by opencast application.
Methods
This retrospective case series screened 36 patients with mallet finger between January 2024 and October 2025. Twelve met the exclusion criteria, leaving 24 eligible patients; eight elected nonoperative treatment, and 16 chose surgery for acute closed tendinous mallet finger and constituted the study cohort. The DIP joint was fixed in approximately 15° of hyperextension using one or two buried 1.1-mm Kirschner wires. An opencast was applied at 1 week. The wires were routinely removed and active motion was initiated at 8 weeks, followed by a removable brace during outdoor or sports activities for 4 weeks. Outcomes were evaluated at 6 months.
Results
The mean preoperative extension lag was 30.0°. At 6 months, the mean residual extension lag was 1.9°, no flexion loss was observed, and Crawford outcomes were excellent in 62.5% and good in 37.5%. Two superficial pin-site infections resolved with oral antibiotics and local wound care. A separate case of wire loosening with painful subcutaneous prominence was managed with an aluminum splint. All patients resumed daily activities and showering at 1 week, when protected sports were also permitted; exact return dates and activity intensity were not recorded.
Conclusions
Buried Kirschner-wire fixation followed by opencast application may be an option for selected patients who wish to avoid prolonged full-time splinting. The protocol permitted protected activities from week 1 and active DIP motion from week 8; these findings support its feasibility but do not establish earlier return to unrestricted activity. Level of evidence: IV.
- 50 View
- 2 Download

Review Article
- Current concepts and applications of internal fixation for forearm diaphyseal fractures
- Sung Yoon Jung, Min Kyun Cho, Dong-hee Kim, Sang Hyun Lee
- J Musculoskelet Trauma 2026;39(3):205-215. Published online July 3, 2026
- DOI: https://doi.org/10.12671/jmt.2026.00087
-
Abstract
PDF
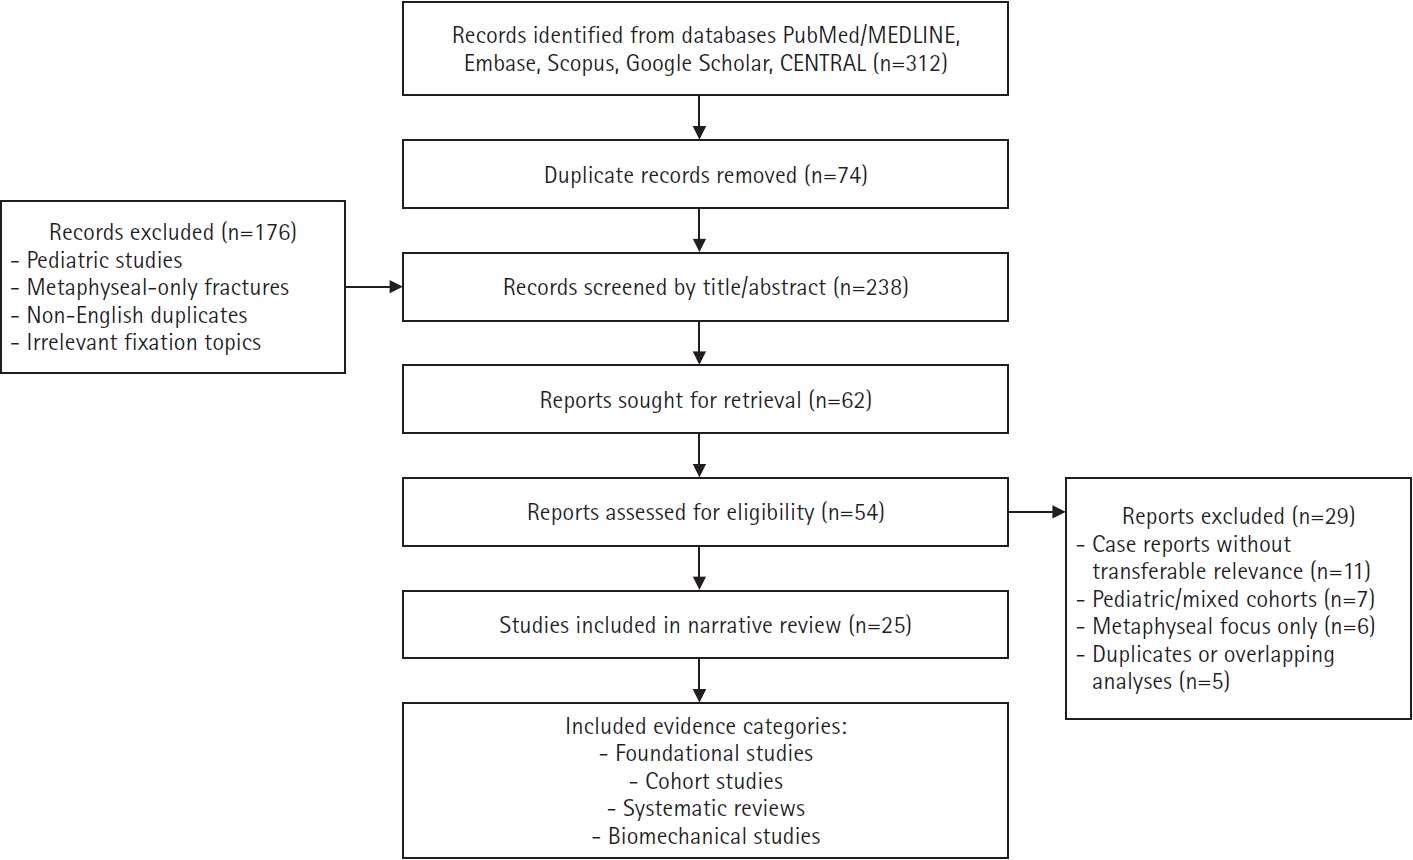
- Adult diaphyseal fractures of the forearm functionally behave as intra-articular injuries because forearm rotation depends on accurate restoration of length, axial alignment, rotation, and the native radial bow. This narrative review summarizes contemporary surgical options for adult forearm shaft fractures, including 3.5-mm plate osteosynthesis, dual mini-plate fixation, interlocking intramedullary nailing, and minimally invasive plate osteosynthesis (MIPO). Compression plating with 3.5-mm plates remains the reference standard for most fracture patterns, whereas other techniques should be regarded as selective, emerging, or salvage options according to their indication spectrum and evidence base. Mini-fragment dual plating may be useful for short segments or thin soft-tissue envelopes, although the supporting clinical evidence remains limited and meticulous biomechanical execution is essential. Interlocking intramedullary nailing is a viable alternative for carefully selected simple fracture patterns or soft-tissue-compromised situations, offering less invasive exposure but a narrower indication spectrum. MIPO may be considered for selected comminuted or soft-tissue-compromised diaphyseal fractures; however, its use in adult forearm fractures remains constrained by the high functional requirement for precise restoration of length, rotation, and the radial bow. To improve transparency, this review explicitly distinguishes established, evidence-supported methods from techniques supported mainly by limited retrospective data or institutional experience. A pattern-based pragmatic algorithm and expanded comparison table are provided to guide fixation selection according to the bone involved, fracture location, fracture morphology, soft-tissue condition, and evidence tier while minimizing complications such as nonunion, infection, nerve injury, refracture after plate removal, and radioulnar synostosis.
- 1,268 View
- 42 Download
 First
 Prev



