-
Impact of posterior wall involvement and fixation on clinical and radiographic outcomes of associated both-column acetabular fractures: a systematic review and meta-analysis
-
Chul-Ho Kim, Eic Ju Lim
-
J Musculoskelet Trauma 2026;39(4):310-322. Published online October 19, 2026
-
DOI: https://doi.org/10.12671/jmt.2026.00248
-
-
 Abstract  PDF  Supplementary Material
- Background
Posterior wall (PW) fractures are frequently associated with both-column (ABC) acetabular fractures. However, whether the presence of a PW fragment or the need for internal fixation affects prognosis remains a topic of debate. This study compared postoperative outcomes, including reduction quality and clinical results, according to the presence of an associated PW fracture and whether PW fixation was performed.
Methods
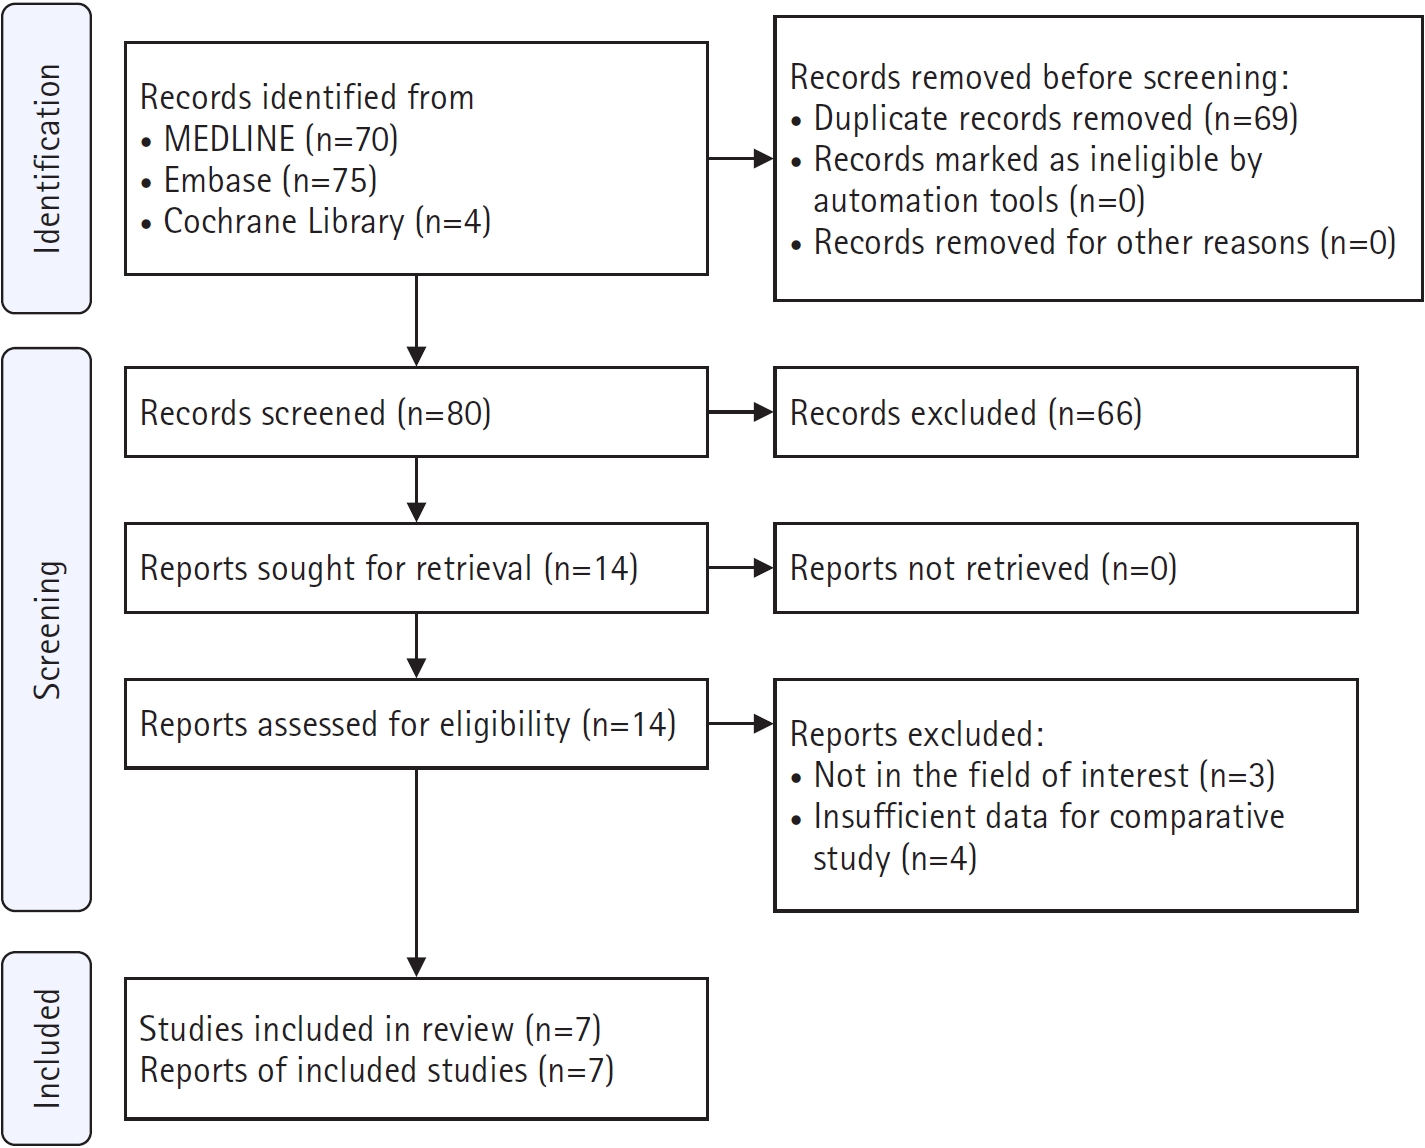
This systematic review and meta-analysis followed the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) 2020 guidelines. MEDLINE, Embase, and the Cochrane Library were searched for articles published up to December 10, 2025. Comparative studies of ABC fractures were included if they evaluated the presence or absence of PW involvement or compared internal fixation with nonfixation of the PW component. Clinical and radiographic outcome data were extracted.
Results
Seven retrospective studies including 434 analyzable patients were included. No clear differences were found in the odds of poor reduction (odds ratio [OR], 0.91; 95% confidence interval [CI], 0.43–1.94; P=0.80), osteoarthritis (OR, 1.04; 95% CI, 0.37–2.92; P=0.94), or conversion to total hip arthroplasty (OR, 0.63; 95% CI, 0.23–1.71; P=0.36) according to the presence of a PW fragment in ABC fractures. Among ABC fractures with PW involvement, nonfixation was associated with numerically higher odds of poor reduction than fixation, although the difference was not statistically significant (OR, 1.47; 95% CI, 0.46–4.76; P=0.52). In unadjusted comparisons of non-randomized cohorts, PW fixation was associated with significantly longer operative time (mean difference [MD], 70.38 min; 95% CI, 24.46–116.29; P=0.003) and greater intraoperative blood loss (MD, 351.36 mL; 95% CI, 244.97–457.74; P<0.00001). The final modified Merle d'Aubigné-Postel score did not differ significantly between the fixation and nonfixation groups (MD, 0.58 points; 95% CI, −0.57 to 1.74; P=0.32).
Conclusions
Current evidence does not clearly support routine fixation of all PW fragments. In unadjusted comparisons of non-randomized cohorts, patients who underwent PW fixation had longer operative time and greater blood loss. These differences cannot be attributed to fixation itself because of confounding by indication and the frequent use of an additional posterior approach. Selective fixation based on residual displacement, joint congruency, and hip stability appears reasonable, although the certainty of evidence remains limited.
Level of evidence: Not applicable.
-
Risk factors of surgical complications after use of the femoral neck system: a random forest analysis
-
Chul-Ho Kim, Hyun-Chul Shon, Han Soul Kim, Ji Wan Kim, Eic Ju Lim
-
J Musculoskelet Trauma 2025;38(3):160-167. Published online July 23, 2025
-
DOI: https://doi.org/10.12671/jmt.2025.00157
-
-
Abstract
PDF
- Background
The femoral neck system (FNS), a novel fixation device for managing femoral neck fractures (FNFs), has gained popularity in recent years. However, analyses of the surgical complications and reoperation risks associated with the use of FNS remain limited.
Methods
This retrospective observational study analyzed 57 patients who had undergone FNS fixation for FNF at two university hospitals between July 2019 and February 2024. Demographic, perioperative, and outcome variables, including age, sex, fracture classification (Garden, Pauwels, and AO), implant characteristics, tip-apex distance (TAD), neck shortening, and neck-shaft alignment, were analyzed. In addition to univariate analysis, a machine learning analysis was conducted using a random forest classifier with stratified sampling (80% training, 20% testing). The accuracy, precision, recall, F1-score, and area under the receiver’s operating curve were calculated to assess model performance.
Results
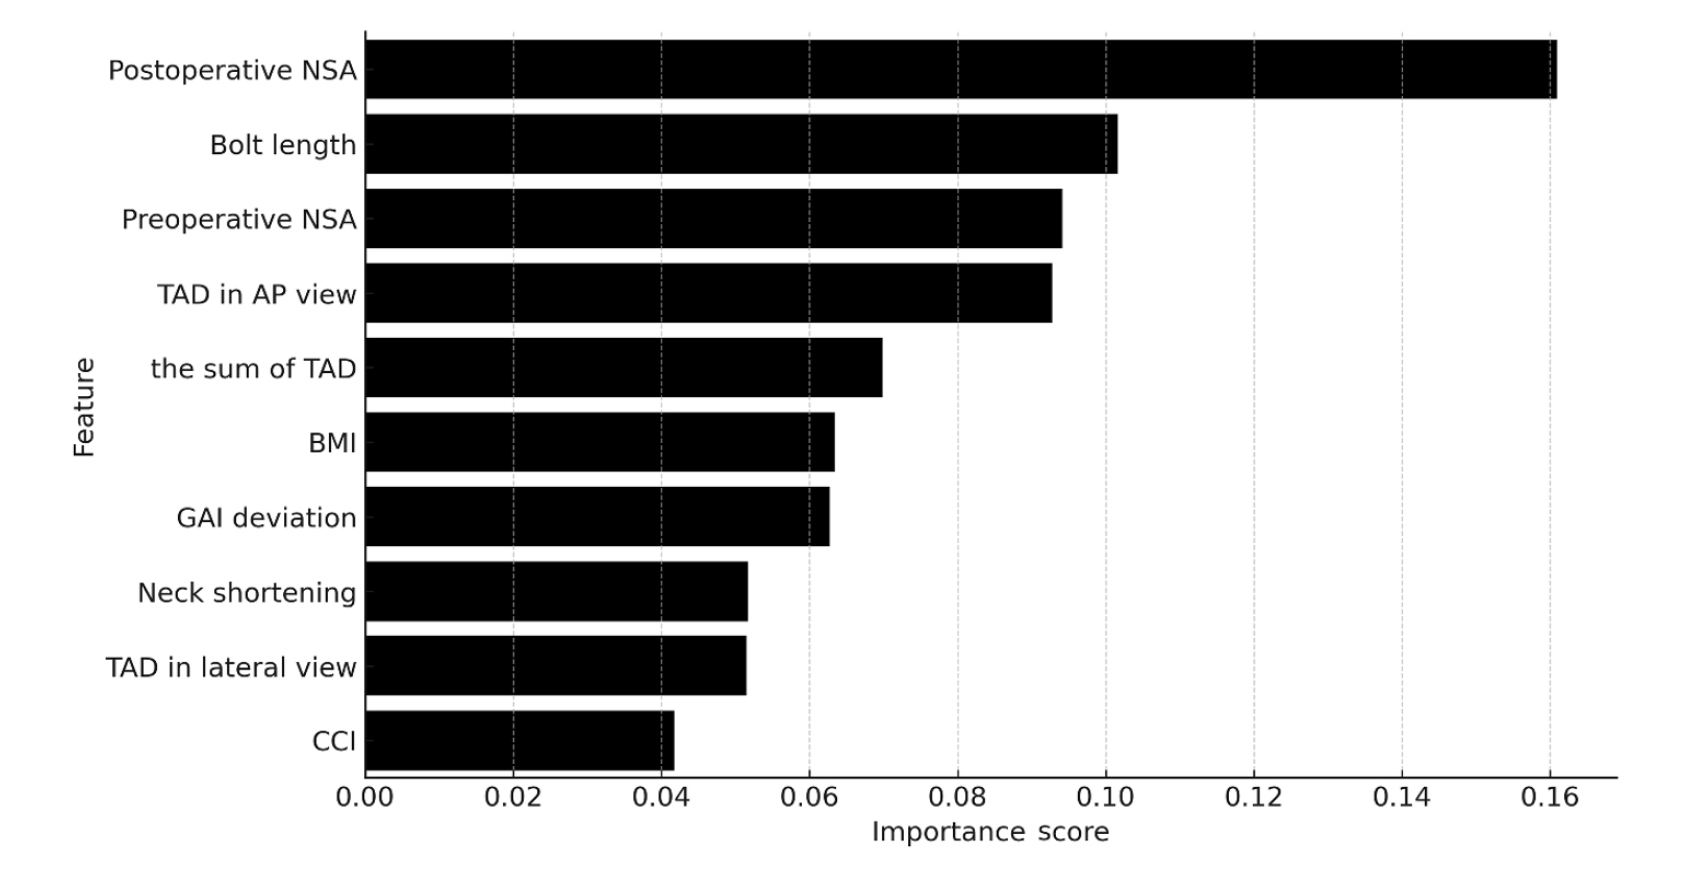
Ten patients experienced osteonecrosis of the femoral head (n=6), implant cut-out or penetration (n=3), and peri-implant fracture (n=1). Univariate analysis revealed that the TAD in the complication group was significantly shorter than that in the control group (12.1 vs. 16.7 mm; P=0.012). Additionally, neck shortening in the complication group was greater than that in the control group (4.9 vs. 2.3 mm; P=0.011). The random forest model achieved an accuracy of 83.3% and identified postoperative neck-shaft angle (NSA) as the most important predictor of complications (feature importance, 0.161), followed by bolt length (0.102) and preoperative NSA (0.094).
Conclusions
Risk factor analysis conducted using a random forest model identified postoperative NSA as the most important feature associated with postoperative complications following FNS. Therefore, care should be taken to normalize the postoperative NSA during FNF surgery.
Level of Evidence: III.
-
Citations
Citations to this article as recorded by  - Length-stable fixation reduces femoral neck shortening in unstable femoral neck fractures: A retrospective comparative study of length-stable dynamic hip screw versus femoral neck system fixation
Seonghyun Kang, Wonseok Choi, Jeong Seok Choi, Eic Ju Lim, SungJin Ahn, Jong-Keon Oh, William T. Kent, Whee Sung Son, Jae-Woo Cho
Journal of Orthopaedic Surgery.2026;[Epub] CrossRef - Characteristics of the Extent and Onset of Osteonecrosis of the Femoral Head After Femoral Neck System (FNS) Fixation: A Minimum Two-Year Follow-Up Comparative Study with Cannulated Screws
Incheol Kook, Sihoon Choi, Soo-Young Jeong, Kyu Tae Hwang
Journal of Clinical Medicine.2026; 15(16): 6405. CrossRef
-
3,628
View
-
65
Download
-
2
Crossref
-
The Role of Beta-Tricalcium Phosphate Graft in the Dynamic Hip Screw Fixation of Unstable Intertrochanter Fracture
-
Chul Ho Kim, Ji Wan Kim, Eic Ju Lim, Jae Suk Chang
-
J Korean Fract Soc 2016;29(4):250-257. Published online October 31, 2016
-
DOI: https://doi.org/10.12671/jkfs.2016.29.4.250
-
-
Abstract
PDF
- PURPOSE
The purpose of this study was to introduce our method of stabilizing unstable intertrochanteric fractures by using the dynamic hip screw (DHS) with a beta-tricalcium phosphate (β-TCP) graft and to compare the outcomes of this procedure with those of the conventional DHS without β-TCP.
MATERIALS AND METHODS
Patients who underwent surgery by using DHS between March 2002 and January 2016 were retrospectively reviewed for analysis of the outcomes. The inclusion criteria were: 1) age of 60 years and older; 2) low-energy fracture resulting from a fall from no greater than the standing height; 3) multifragmentary pertrochanteric fracture (AO classification 31-A2.2, 2.3); and 4) follow-up of over 3 months. We compared 29 patients (29 hips) who underwent surgery, using DHS without β-TCP, with 29 age-sex matched patients (29 hips) who underwent surgery using DHS with grafted β-TCP granules to empty the trochanter area after reaming. We investigated the fracture union rate, union time, and length of lag screw sliding.
RESULTS
Bone union was achieved in all cases. The mean union time was 7.0 weeks in the β-TCP group and 8 .8 weeks in the non-β-TCP group. The length of lag screw sliding was 3.6 mm in the β-TCP group and 5 .5 mm in the non-β-TCP group. There were no implant failure cases in both groups.
CONCLUSION
The β-TCP graft for reinforcement DHS acquired satisfactory clinical outcomes for treating unstable intertrochanteric fractures.
|

 E-submission
 KOTA
 TOTA
 TOTS